
Direct Superior Hip Replacement
Direct superior hip replacement is a minimally invasive muscle-sparing approach that accesses the hip joint through a single small incision at the side of the hip. Unlike the posterior approach, it does not cut the short external rotator tendons, and unlike traditional lateral approaches, it preserves the gluteus medius and minimus muscles.

Understanding Your Procedure
In-Depth: Direct Superior Hip Replacement
A clear, comprehensive look at what this procedure is, how it works, and why it may be the right choice for you.
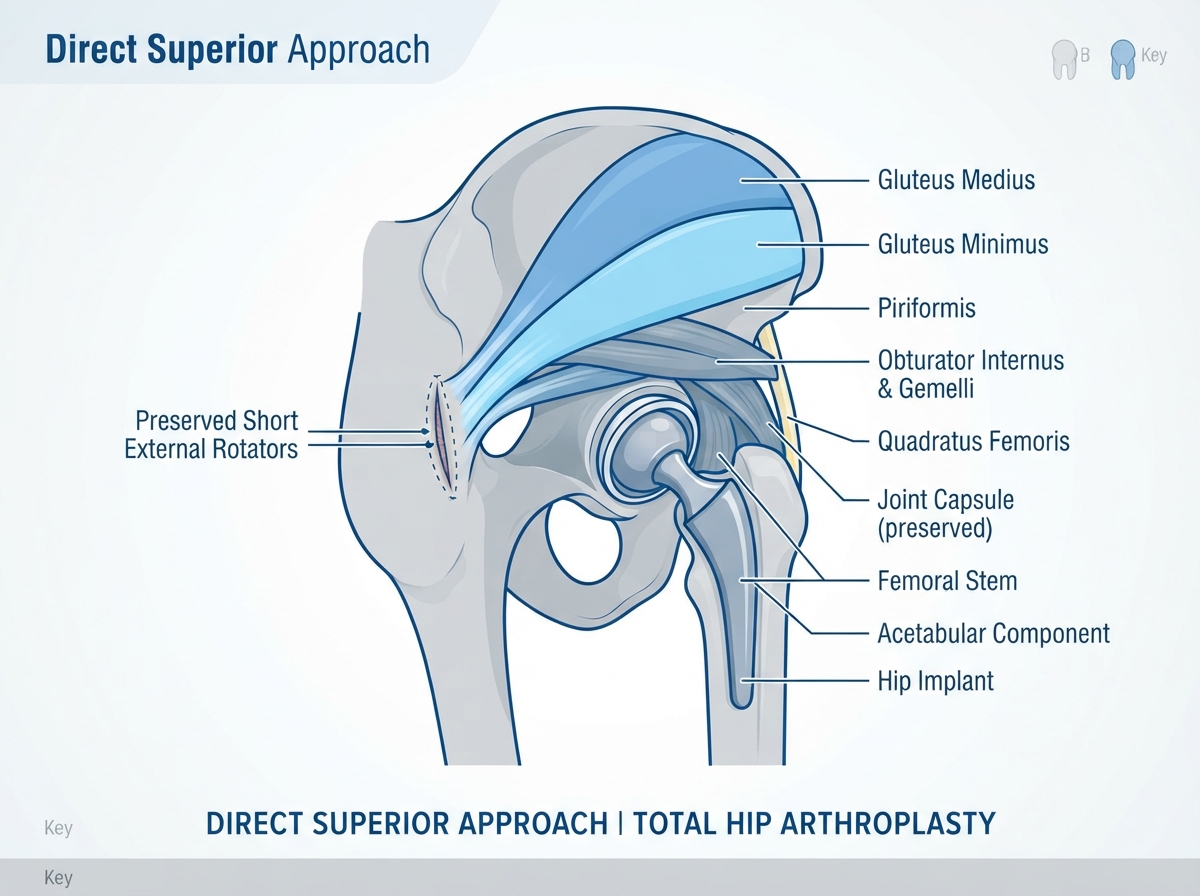
Direct Superior Hip Replacement — illustrated overview of the surgical approach and implant placement.
What Makes This Approach Different
Short External Rotator Preservation
Unlike the posterior approach, the does not cut the short external rotator tendons, eliminating the need for and reducing risk.
Abductor Muscle Preservation
Unlike the lateral (Hardinge) approach, the gluteus medius and minimus are preserved, preventing the persistent limp that can result from abductor damage.
Single Small Incision
The procedure is performed through one small incision at the side of the hip, typically 3-4 inches, resulting in less tissue trauma and smaller scar.
No Hip Precautions
Because the posterior capsule and rotators are preserved, there are no restrictions on bending, crossing legs, or sitting positions after surgery.
Clinical information reviewed and edited by Dr. Ali H. Sobh, MD, board-certified orthopedic surgeon. Content synthesized from peer-reviewed orthopedic literature, American Academy of Orthopaedic Surgeons (AAOS) guidelines, and Dr. Sobh's fellowship training at Rush University Medical Center. Last updated 2025.
Watch & Learn
Understanding the Direct Superior Approach
These physician-led videos explain how the direct superior approach combines the muscle-sparing benefits of anterior surgery with the familiarity of a posterior incision — offering less blood loss, less pain, and faster recovery.
Minimally Invasive Hip Surgery — Direct Superior
Dr. Ford of Campbell Clinic Orthopaedics explains the direct superior approach — a minimally invasive posterior technique that takes the benefits of the anterior approach while mitigating its downsides. He compares all major hip approaches and explains why this muscle-friendly technique is gaining popularity.
Superior Approach — Patient Benefits
Dr. Gary Willstein of Providence explains how the superior approach is less invasive with less blood loss and less pain after surgery. Patients get up and walk the day of surgery and recover more quickly compared to traditional approaches.
Dr. Sobh's Direct Superior Expertise
Videos embedded from YouTube for patient educational purposes. Dr. Dr. Ali H. Sobh, MD reviews all educational content on this page. Sources: Campbell Clinic Orthopaedics (Dr. Ford) and Providence (Dr. Gary Willstein, MD).
Interactive Education
See How Your Joint Works
Understanding your condition is the first step toward confident decisions. Use this interactive visualizer to explore the anatomy of the hip joint, compare a healthy joint with an arthritic one, and see exactly what direct superior hip replacement restores.
- 1Toggle states to compare healthy, arthritic, and post-surgical joints.
- 2Tap the dots to learn about each anatomical structure.
- 3Watch the motion to see how the joint moves during activity.
Interactive Joint Visualizer
Explore how direct superior hip replacement works
Recognizing the Signs
Common Symptoms
Many patients live with joint pain for years before seeking treatment. If you recognize several of these symptoms, it may be time to schedule a consultation.
When to seek care
Why Dr. Sobh for This Procedure
Fellowship-Trained Expertise in Direct Superior Hip Replacement
Dr. Sobh's fellowship training included the as part of his comprehensive training in muscle-sparing hip surgery. He offers this approach to patients who may not be ideal candidates for the —such as very muscular patients or those with specific anatomical considerations—while still achieving a muscle-sparing, tendon-preserving result. His expertise in multiple approaches allows him to select the optimal technique for each patient's unique anatomy.
Conditions Treated
Is Direct Superior Hip Replacement Right for You?
Dr. Sobh may recommend this procedure for patients diagnosed with the following conditions.
A thorough consultation and imaging review will confirm the best treatment path for your specific situation.
Are You a Candidate?
Candidacy for Direct Superior Hip Replacement
Dr. Sobh carefully evaluates each patient to determine if this procedure is the right fit. Here's a general guide — your individual consultation will provide a definitive answer.
Patients with severe hip arthritis who want a muscle-sparing approach but may not be ideal candidates for the direct anterior approach due to body habitus or anatomy.
Patients who want to avoid hip precautions after surgery and minimize dislocation risk.
Patients with prior posterior hip surgery may require the same approach for revision. Patients with severe deformity may need a different approach.
Patients with active hip infection or severe vascular disease need to resolve those conditions before any elective joint replacement.
Technology & Techniques
Advanced Technology Used in Your Surgery
Dr. Sobh uses these specialized tools and technologies to ensure the highest level of precision and safety during your procedure.
Specialized Superior Approach Table
A specialized orthopedic table allows precise positioning of the leg during surgery, similar to the anterior approach, enabling optimal access through the small incision.
Intra-Operative Fluoroscopy
Real-time X-ray imaging confirms implant position, leg length, and cup alignment through the small incision.
Muscle-Sparing Retractors
Specialized retractors allow access to the hip joint through the superior capsule without detaching muscles or tendons.
How the Surgery Works
Understanding Your Surgical Journey
From your first consultation to full recovery, here's what to expect at each stage. Dr. Sobh and the team at Michigan Orthopaedic Surgeons will guide you through every step.
Pre-Operative Planning
X-rays and templating plan size and alignment. Dr. Sobh determines if the is appropriate for your anatomy.
Superior Capsulotomy
Through a single small incision at the side of the hip, Dr. Sobh accesses the joint through the superior capsule without cutting muscles or detaching the short external rotator tendons.
Implant Placement
The damaged ball and socket are replaced with biocompatible implants. Intra-operative confirms precise position and leg length.
Rapid Recovery
Because no muscles or key tendons are cut, patients walk with assistance on the day of surgery and experience a fast, comfortable recovery without .
Recovery Timeline
Your Path Back to Activity
Recovery timelines vary by individual and procedure complexity. Dr. Sobh will provide a personalized rehabilitation plan. Here's a general guide to what most patients experience.
Day of Surgery
Stand and walk with assistance. No hip precautions. Begin gentle movements. Most patients go home within 24 hours.
Early Recovery
Walk with a walker or cane. Return to light activities. No restrictions on sitting or sleeping positions.
Progressive Activity
Transition off walking aids. Resume driving and office work. Therapy advances to strengthening and balance.
Full Recovery
Return to low-impact sports and activities. Near-complete pain relief with preserved muscle function.
Comparing Your Options
Direct Superior Hip Replacement vs. Alternatives
Understanding how direct superior hip replacement compares to other treatment options helps you make an informed decision. Dr. Sobh will discuss all viable options during your consultation.
Direct Anterior Hip Replacement
The anterior approach accesses the hip from the front. The accesses from the side. Both are muscle-sparing, but the superior approach may be preferred for patients whose anatomy makes the anterior approach technically difficult.
Posterior Hip Replacement
The posterior approach cuts through the short external rotator tendons and requires for 6-12 weeks. The preserves these tendons, eliminating precautions and reducing risk.
Anterolateral (Hardinge) Approach
The anterolateral approach splits the gluteus medius and minimus, which can cause a persistent limp. The preserves these abductor muscles completely.
Patient Journey Tip
Benefits
This procedure offers significant advantages for qualified patients:
- No muscle or tendon cutting
- No hip precautions after surgery
- Lower dislocation risk than posterior approach
- Single small incision with minimal scarring
- Preserved abductor muscles prevent limp
- Faster recovery than traditional approaches
Potential Risks
As with any surgery, there are potential risks. Dr. Sobh takes extensive measures to minimize them:
- Infection (rare)
- Blood clots—prevented with medication and early walking
- Leg length discrepancy
- Implant loosening over time
- Dislocation (low, similar to anterior approach)
- Anesthesia-related risks
Important
Patient Questions
Frequently Asked Questions
Common questions patients ask about direct superior hip replacement.
How is the direct superior approach different from the direct anterior approach?
How is the direct superior approach different from the direct anterior approach?
Both are muscle-sparing approaches. The anterior approach accesses the hip from the front; the accesses from the side. The superior approach may be preferred for patients whose anatomy makes the anterior approach difficult, while still preserving muscles and tendons.
Are there hip precautions after direct superior hip replacement?
Are there hip precautions after direct superior hip replacement?
No. Because the short external rotator tendons and posterior capsule are preserved, there are no restrictions on bending, crossing legs, or sitting positions after surgery—similar to the anterior approach.
Is the recovery similar to the anterior approach?
Is the recovery similar to the anterior approach?
Yes. Because both approaches are muscle-sparing, the recovery timeline is similar. Patients walk on the day of surgery, go home within 24 hours, and return to activities without precautions.
Why would I choose the direct superior approach over the anterior approach?
Why would I choose the direct superior approach over the anterior approach?
Dr. Sobh may recommend the if your anatomy or body habitus makes the anterior approach technically challenging. Both are excellent muscle-sparing options, and Dr. Sobh will recommend the best approach for your specific case.
This procedure page was clinically reviewed and approved by Dr. Ali H. Sobh, MD, a board-certified, fellowship-trained orthopedic surgeon specializing in direct anterior hip replacement and MAKO robotic knee surgery. Dr. Sobh graduated with high honors from Wayne State University School of Medicine and completed his adult reconstruction fellowship at Rush University Medical Center in Chicago. He practices at Michigan Orthopaedic Surgeons (MOS) with offices in Royal Oak and Southfield, Michigan.
This information is for educational purposes only and is not a substitute for professional medical advice. Individual results and recovery timelines vary. Schedule a consultation with Dr. Sobh to discuss your specific condition and treatment options.

Ready to Take the Next Step?
Schedule a personalized consultation with Dr. Sobh to discuss whether direct superior hip replacement is right for you. Our team will help coordinate your visit, insurance verification, and pre-operative planning.
Explore More
Related Procedures
Direct Anterior Hip Replacement
Minimally invasive muscle-sparing hip replacement with no muscle cutting for faster recovery.
Revision Hip Replacement
Complex reconstructive surgery to correct failed, worn, or infected prior hip replacements.
Total Hip Replacement
Complete hip joint reconstruction replacing both the femoral head and acetabulum with durable biocompatible implants.
Helpful Patient Resources